Patients ask whether their acne scars can be removed. Treatability is the more informative question, because it varies between individual scars on the same face and determines both the improvement that is realistic and the cost of obtaining it. The scar types are ranked below from those that respond best to those that respond least, with the trial figures reported for each. Classification and grading are set out separately in the types of acne scars, and the full treatment plan in the acne scar treatment guide.
Dr Gerard Ee consults at The Clifford Clinic, 50 Raffles Place, Singapore.
For what each scar type is and how to recognise it, see types of acne scars explained.

Acne scar treatability, ranked by type
There are three main types of depressed acne scars: rolling, boxcar and ice pick. Each type needs a different first procedure: subcision for rolling scars, fractional CO2 or RF microneedling for boxcar scars, and TCA CROSS for ice pick scars. Flat red or brown marks are not scars and are treated with V Beam or Q-Switch.
| Easiest | Rolling scars. Once released with subcision, they respond better than any other type in the comparative trials. |
| Good | Boxcar scars, shallow to medium. Resurfacing and radiofrequency (RF) microneedling remodel them effectively, and combinations outperform either treatment alone. |
| Harder | Ice pick scars. No laser reaches the floor of the pit. TCA CROSS placed into each scar produces substantial improvement in most patients, although every pit is treated individually. |
| Hardest | Deep boxcar scars and wide tethered scars in thick facial tissue. Any scar in skin that pigments easily is equally difficult, because the limit is set by what the skin safely tolerates rather than by the scar. |
| Different pathology | Keloid and hypertrophic scars. These represent excess collagen rather than a deficit, and the treatments above can make them worse. |
Rolling scars, the easiest to treat once released
A rolling scar is a shallow depression with no defined edge, tethered from below by fibrous bands. No treatment applied at the surface will lift it while the band remains intact, and once the band is divided, the skin rises without further intervention. Subcision, in which a needle or blunt cannula is passed beneath the scar to release it, therefore has the widest reported range of improvement of any single scar treatment, from 10 to 100 per cent depending on the series [1]. In a 2024 randomised split-face trial comparing subcision alone with subcision plus a hyaluronic acid gel, the rolling subtype responded best in both arms, and scar depth fell by approximately 29 per cent on ultrasound after a single treatment [2].
The effect of subcision alone is modest. The larger gains come from combining it with a treatment that prevents the released band from re-forming. In a 40-patient randomised trial, subcision followed either by fractional CO2 laser or by a hyaluronic acid filler outperformed subcision alone on blinded scoring, with no difference between the two additions [3]. In practice I release the band and place a biostimulator or RF microneedling over it, which applies the same principle, holding the tissue free of tethering while new collagen forms.
Boxcar scars, good responders that improve further with combinations
Boxcar scars have steep walls and a flat floor. Shallow and medium boxcar scars respond well to any treatment that remodels the dermis, namely fractional CO2, RF microneedling, or the two in sequence. The largest analysis to date, a 2026 network meta-analysis of 56 randomised trials and 1,488 patients across 34 treatments, found that combinations consistently outperformed single treatments for moderate-to-severe atrophic scars, and that fractional CO2 with subcision, or with platelet-rich plasma (PRP), gave the most consistent benefit [4]. A 2025 analysis of 68 trials and 4,480 patients reached the same conclusion from a different dataset, in which laser combined with a second modality, whether PRP, a filler or a peel, ranked above laser alone on every outcome [5].
Fractional CO2 against RF microneedling is the comparison most patients face. A 2026 meta-analysis of the head-to-head randomised trials found CO2 slightly more effective and slightly better rated by patients, but with about two points more pain on a ten-point scale, redness lasting nearly two days longer, and four times the risk of post-inflammatory darkening [6]. In Singaporean skin that trade-off governs the choice for a boxcar scar, and it is examined again below.
Ice pick scars, resistant to laser and responsive to acid
An ice pick scar is a narrow pit that extends deep into the dermis, and a laser or needle acting at the surface does not reach its floor. The technique that does reach it is TCA CROSS, in which a drop of concentrated trichloroacetic acid is placed into each pit to collapse and rebuild it. In the systematic review of non-energy treatments, TCA CROSS produced more than 70 per cent improvement in 73 per cent of patients, the highest figure for any technique in that review [1]. Treatment proceeds pit by pit and requires repetition, and because the number of pits determines the time and cost involved, the treatment is quoted at consultation.
Ice pick scars present a second difficulty. They are the scars most often left behind after a course of resurfacing has improved everything else, and that residue is commonly interpreted as treatment failure. It is not a failure of the course, but a scar that required a different technique from the outset.
Why the hardest acne scars respond least
Deep, wide, tethered scars in thick facial tissue
Scars that are both deep and broad, with tethering beneath and thick tissue above, respond least to any single course of treatment. Depth and tethering set that limit, because a resurfacing laser remodels only the upper dermis its energy reaches, while the fibrous attachment holding the floor of the scar down sits below that level. In a retrospective series of 107 Asian patients treated with fractional CO2 for acne scars, two in three improved by less than 25 per cent after their course and only one in twenty improved by more than half [7]. Those figures describe a laser used alone in this skin type, and they are the reason a difficult face is planned as a six-month combination programme rather than around a single device. The realistic expectation for a well-planned course is a 20 to 30 per cent improvement with energy-based treatment, and more where biostimulators are added. That expectation is set out in the guide.
Any scar in skin that pigments easily
For most Singaporeans the ceiling on scar treatment is set by post-inflammatory hyperpigmentation rather than by the scar itself. In the Asian CO2 series, darkening was the commonest side effect [7]. In the head-to-head meta-analysis, CO2 carried four times the darkening risk of RF microneedling [6]. In a randomised split-face trial in Thai patients, fractional CO2 caused mild darkening in one in four, whereas a fractional picosecond laser on the opposite side achieved the same result with none [8]. Two measures reduce that risk. The first is selection of the device, namely insulated RF microneedling as the opening treatment, ablative laser at lower settings, or a picosecond laser in its place. The second is what is applied to the skin afterwards. In a randomised trial of forty Thai patients with type IV skin, two days of a potent steroid ointment after fractional CO2 reduced the darkening rate from 75 per cent to 40 per cent on the treated side of the face [9]. A course conducted at safe settings in darker skin takes longer, and that additional time is the price of avoiding the pigmentation that would otherwise undo the result.
Keloid and hypertrophic scars, a different pathology
Raised scars contain too much collagen rather than too little, so the resurfacing, needling and subcision that improve the atrophic scars described above can make them worse. They are treated instead with intralesional steroid injection, pressure, silicone and selected lasers, and a history of keloids is a reason for caution with aggressive resurfacing anywhere on the face. They are included only to mark the boundary of this article, because none of the treatability ranking above applies to them. The commonest error I see in a previous plan is a device chosen for depressed scars then applied to a raised one, which it cannot improve.
Raised scars that grow beyond the original wound are keloids, a different problem from the pitted scars above; see my guide to keloid scars and the options for keloid treatment in Singapore.
How treatability changes the treatment plan
Most faces carry a mixture of scar types, and the ranking above is the reason a plan treats them in sequence rather than with a single device. Active acne is settled first, because new lesions generate new scars. The rolling scars are then released, since no other treatment is effective while they remain tethered. The boxcar scars are remodelled with RF microneedling or fractional CO2 at settings the patient’s skin tolerates. The ice pick scars are treated individually with TCA CROSS. Where volume loss is genuine, the deficit is rebuilt with a biostimulator. Sessions are spaced four to six weeks apart so that each round of collagen matures before the next is started. That sequence is the method in full, and the guide and the cost page set out what it involves and what it costs.
Atrophic scars, the depressed majority
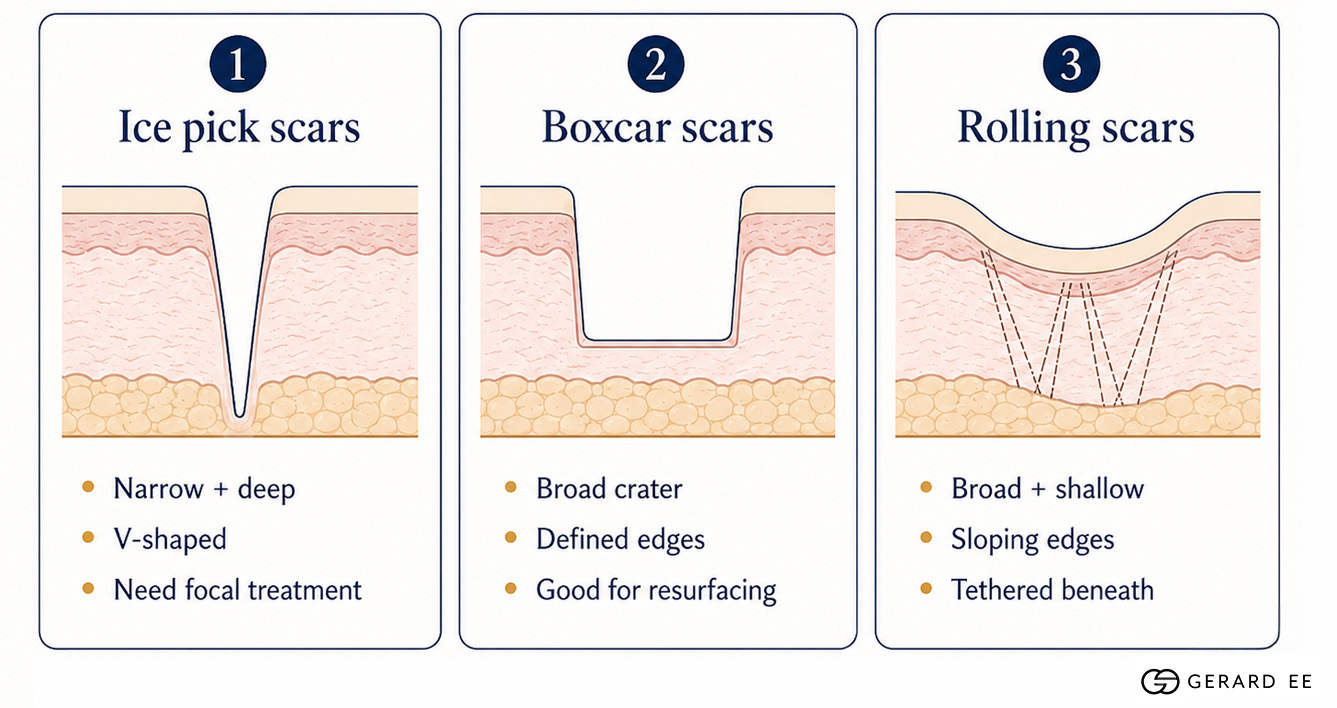
Eight or nine in ten acne scars are atrophic, which means they sit below the level of the surrounding skin. Under angled light, which throws shadows that reveal their shape, they sort into three types, and most faces carry a mixture. The proportions of that mixture determine what a plan must contain.
Ice pick scars
Ice pick scars are narrow, deep and V-shaped, resembling a fine puncture. They reach far into the dermis, which makes them the most resistant of the atrophic types, and they rarely respond to resurfacing or microneedling alone. They require a reconstructive approach, either TCA CROSS, in which acid is applied precisely into the scar to rebuild it from its base, or, in my clinical experience the safer and more effective option, PDLLA skin booster placed into the pit. They are also the type where expectations need setting most carefully, because the improvement available is genuine but partial.
Boxcar scars
Boxcar scars are round or oval with sharp edges, and they are common on the cheeks and temples. They respond well to resurfacing, to energy-based collagen remodelling such as fractional CO2 and RF microneedling, and to biostimulators such as PDLLA skin booster. Depth divides them, since a shallow boxcar scar softens with resurfacing while a deep one with rigid walls needs its base released first.
Rolling scars
Rolling scars are broad and wavy, caused by fibrous bands tethering the skin down. The defining feature is the tether, and resurfacing will not lift the scar until that tether is released with subcision. Subcision is usually paired with a biostimulator such as PLLA, particularly where the skin is also somewhat lax, as covered in the guide to subcision and biostimulators for rolling scars. When a patient reports that a previous course of resurfacing did nothing for the wavy areas of a cheek, an unreleased tether is usually the reason.
Ice pick scars in more detail
Histologically, an ice pick scar is a narrow epithelial tract descending steeply into the deep dermis, and sometimes into the subcutis, tapering to a point. That shape is the reason broad resurfacing underperforms, since a laser or microneedle acting across the surface cannot rebuild the base of so narrow and deep a channel. Focal reconstruction is required instead of surface treatment. TCA CROSS applies a high concentration of trichloroacetic acid precisely into the pit, producing controlled tissue necrosis and a frost, which prompts new collagen to fill the channel from within across successive sessions. Wider or fibrotic ice pick scars may instead be treated with punch excision, and PDLLA skin booster placed into the scar can support the reconstruction. Because the channel fills from its base upwards, the change after any one session is usually slight.
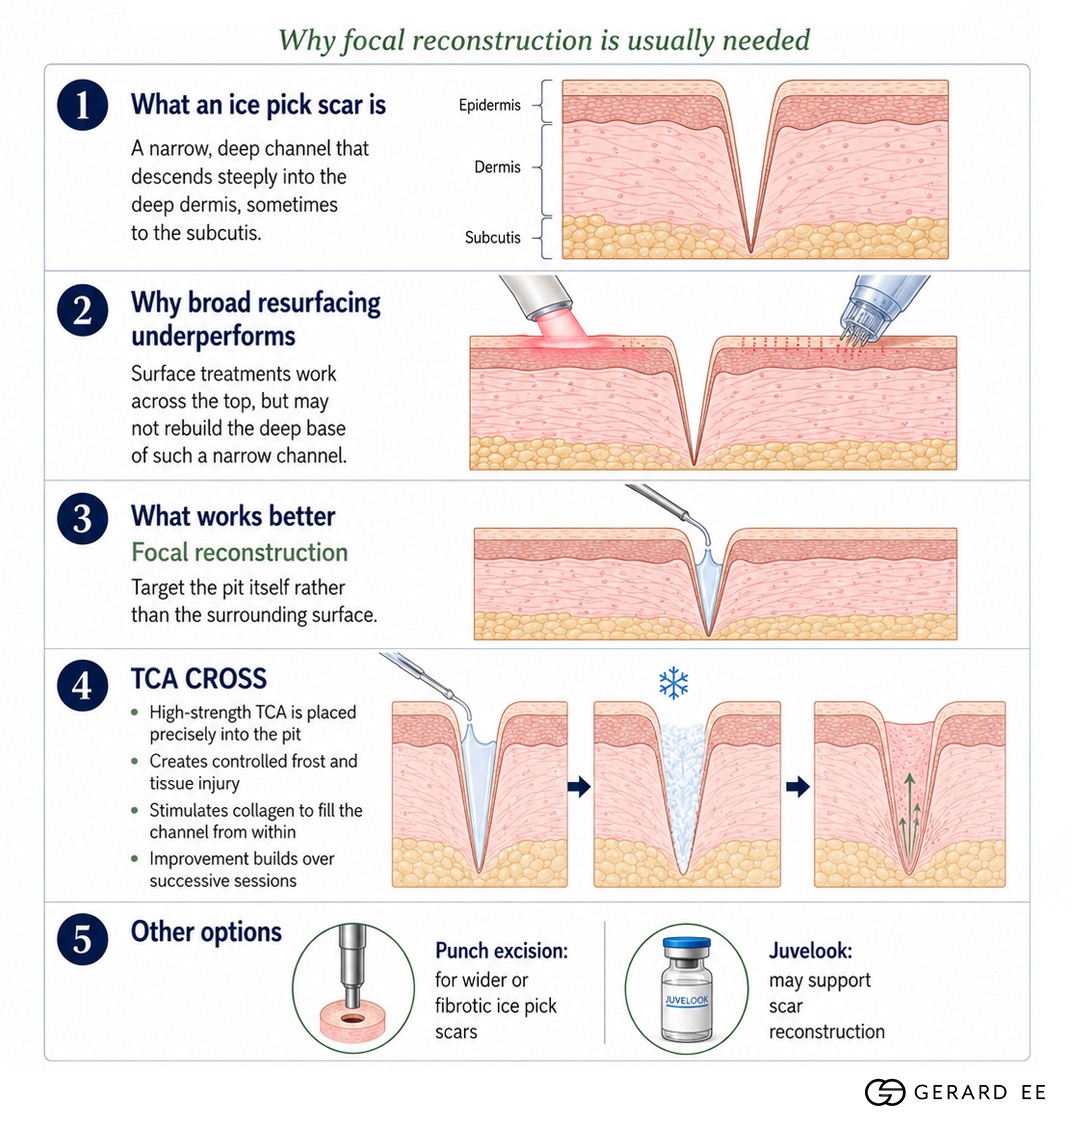
focal reconstruction acne scar
Boxcar scars in more detail
Boxcar scars are round to oval depressions with sharply defined, near-vertical walls, and they resemble the marks of chickenpox. They are classified by depth, shallow at around 0.1 to 0.5 mm and deep at greater than 0.5 mm. Shallow boxcar scars respond well to fractional resurfacing and RF microneedling, both of which remodel collagen and soften the sharp edges. Deeper boxcar scars with rigid walls may need punch elevation, in which the base of the scar is released and raised to sit level with the surrounding skin, then combined with resurfacing and energy-based remodelling. Where resurfacing has softened the shallow boxcar scars on a cheek and left the deep ones unchanged, wall depth is the explanation.
Rolling scars in more detail
Rolling scars are broad, shallow depressions, often 4 to 5 mm across or wider, produced by fibrous bands that tether the skin to the deeper tissue beneath. The surface itself remains relatively intact, so the defining problem is the tethering rather than a loss of surface tissue. Their appearance worsens with facial movement and becomes more noticeable with age as the face loses volume and the tethering grows more prominent. Subcision to divide the bands is essential, after which a biostimulator or energy device builds collagen in the released space and holds the lift. Release is therefore only half the treatment, since the collagen built into that space is what holds the correction over the following months.
Why most faces show a mixture of types
Acne affects many follicles at different depths and over an extended period, which is why a single face usually carries ice pick, boxcar and rolling scars together, often alongside flat marks. No single device therefore suits everyone. The dominant scar type guides the lead treatment, while the rest of the mixture determines what else the plan must contain. In my experience the mixture is also why two patients with similar-looking scarring report very different satisfaction after the same treatment.
What the comparative trials show, by scar type
The trial evidence divides along the same subtypes. In a retrospective analysis of 413 patients, fractional CO2 laser combined with subcision proved significantly more effective than laser alone for boxcar and rolling scars, while making no significant difference for ice pick scars (413-patient analysis). A randomised study likewise found that subcision combined with either fractional CO2 or cross-linked hyaluronic acid outperformed subcision alone, with no significant difference between the two add-ons, which confirms that subcision acts best when paired with something that rebuilds collagen or volume (subcision combination trial). The null result for ice pick scars in that series is its most useful finding, marking a subtype the standard combination may not suit.
Rolling and boxcar scars respond to subcision-plus-energy combinations, while ice pick scars need targeted reconstruction such as TCA CROSS or punch techniques. The 2022 international consensus on energy-based devices reaches the same subtype-specific conclusion (consensus).
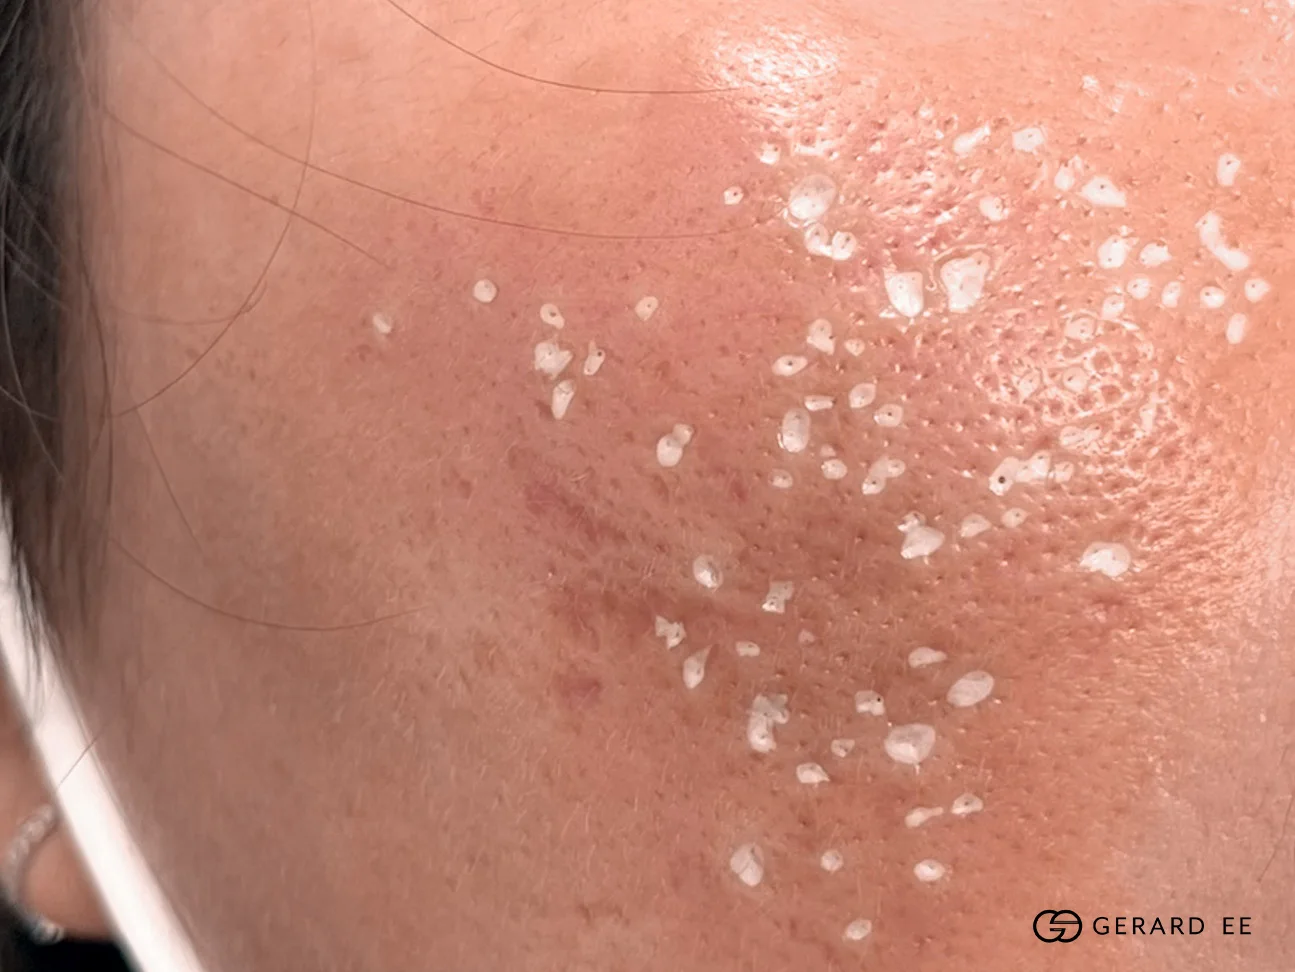
How doctors grade acne scars
Beyond naming the type, clinicians grade scarring to guide treatment and to track progress. The Goodman and Baron qualitative scale sorts scarring into macular (flat, only colour), mild, moderate and severe grades, while their quantitative scale assigns a numerical score from the number and severity of lesions. The ECCA grading scale (Echelle d’Evaluation Clinique des Cicatrices d’acne) weights each scar type instead, scoring deeper and more visible scars more heavily, and is widely used in clinical studies to quantify improvement. A grading system matters because it converts a subjective impression into a consistent baseline, against which it becomes possible to judge whether a course of treatment is genuinely working. A grade measures severity rather than composition, however, and the plan follows the composition.
How scar type is assessed in person
Accurate assessment requires more than a glance in a mirror. Examination under angled light throws shadows that reveal the depth and edges of each scar. Stretching the skin gently shows whether a depression flattens, indicating a shallow or tethered scar, or holds, indicating a fixed structural defect. Palpation detects the firmness of a raised scar and the fibrous tethering beneath a rolling scar. Standardised, well-lit photographs taken at each visit then permit an accurate comparison over time, since gradual collagen remodelling is difficult to judge day to day. I photograph at every review for that reason, because patients judging their skin from memory routinely misjudge how far it has moved.
What the research shows
The literature supports the principle that scar type should drive treatment. For ice pick scars, which are notoriously resistant, TCA CROSS is repeatedly reported as safe, effective and cost-effective (CROSS with 100% TCA, CROSS comprehensive review). A systematic review of randomised trials found microneedling to be efficacious and well tolerated for atrophic scars (microneedling RCT review), and subcision studies show rolling scars among the best responders (subcision split-face study). The same literature is quieter about the scars that respond least, and a resistant ice pick scar may need several sessions of focal reconstruction before change is visible.
How each scar type responds, and why combinations outperform single devices
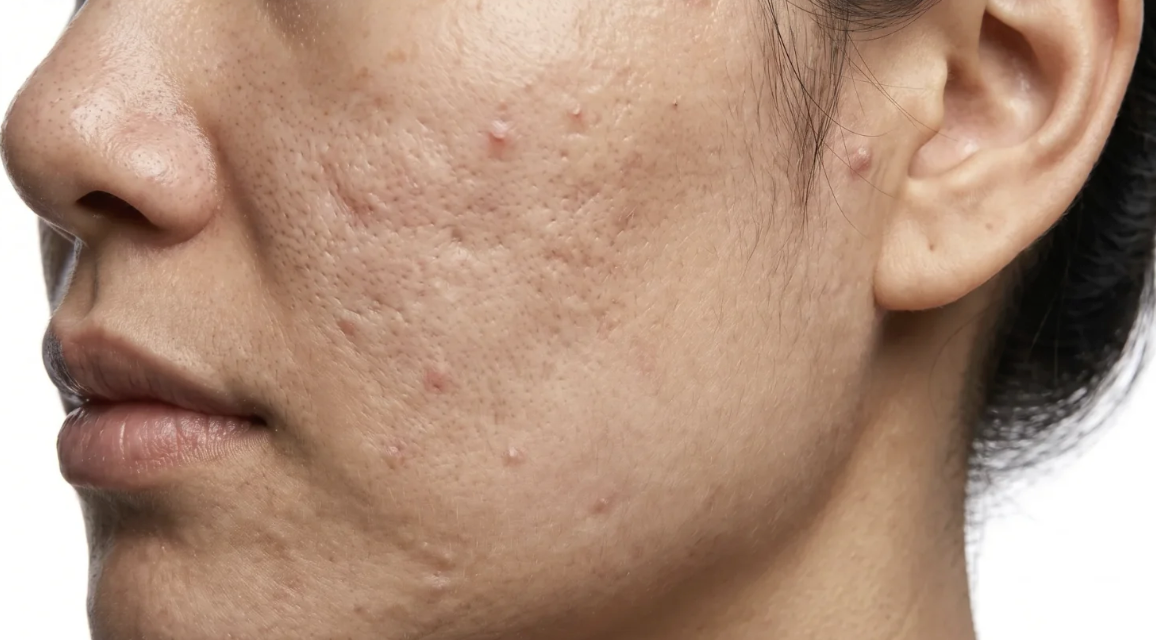
Ice pick scars, the most resistant, respond best to focal reconstruction with TCA CROSS (CROSS review). Boxcar scars respond to resurfacing and energy-based remodelling, and rolling scars to release with subcision, where studies place them among the best responders (subcision study). The literature increasingly favours combinations, with microneedling plus CO2 laser, or subcision plus other modalities, outperforming monotherapy (microneedling and CO2 review). That evidence is firmer on which type responds to which modality than on how much any one patient will improve.
Two faces given the same severity grade can still need different plans. A face that is mostly rolling needs a different sequence from one that is mostly ice pick, and matching the plan to that mix is what the evidence, and my own clinical experience, indicate drives the best result.
Which of these are easy and which are hard is ranked in which acne scars are hardest to treat.
Matching biostimulators to the scar
Where volume and collagen support are needed, the biostimulator is chosen to fit the scar rather than one product being used for everything. PCL suits significant volume loss, PDLLA skin booster suits ice pick and boxcar scars, PLLA or PDLLA Volume suit rolling scars with loose skin, and ECM booster suits very mild scarring. PDRN, Rejuran, may be added across the board because it improves healing and supports the wider result, and it can be performed alongside microneedle RF. No biostimulator used on its own releases a tether or rebuilds an ice pick scar, so each belongs within a plan rather than in place of release and resurfacing.
Why almost everyone needs a combination
Because a single face usually carries rolling, boxcar and a few ice pick scars together, treating all of them with one machine inevitably leaves part of the problem behind. Mapping the mix and building a layered plan follows from that, with subcision for the tethers, TCA CROSS or PDLLA skin booster for the ice pick scars, and resurfacing and RF for the boxcar scars and overall texture. Of the patients who consult me after a course they judged to have failed, a substantial number had received one treatment only, usually a weak microneedle fractional RF machine, or, as is common, Rejuran placed on the scar in the belief that it will help collagen growth. The proportions are the foundation of the complete treatment guide.
Confirm it is a scar, not a mark
Confirming that what is present is a true scar, and not a flat brown or red mark that fades differently, comes before any commitment to scar treatment. The guide to acne scars versus pigmentation explains the quick stretch-and-light test, and what causes acne scars describes how they form in the first place. A flat mark treated as a scar absorbs resurfacing it never needed, and a scar dismissed as a mark waits for a fading that never comes.
Punch techniques for resistant scars
Some deep or sharply defined scars respond best to small surgical techniques that reshape the scar directly rather than to any device applied across the surface. Punch excision removes a narrow, deep ice pick or steep boxcar scar entirely with a tiny circular tool, and the edges are then closed to heal as a much finer line that can later be resurfaced. Punch elevation raises the base of a deep boxcar scar with intact walls to the level of the surrounding skin, which preserves the patient’s own tissue and colour while removing the shadow that made the scar visible. Punch grafting fills a scar with a small graft of skin taken from another site. These techniques are precise, and they are usually followed by resurfacing or energy-based treatment to blend the result into the surrounding skin. Each substitutes a smaller and more regular mark for an irregular one rather than removing the scar without trace.
What the published evidence on PDLLA skin booster for atrophic scars shows
PDLLA skin booster has been combined with carbon dioxide gas subcision for atrophic acne scars in a published series, which is the hybrid mechanical-plus-biologic approach I use for rolling scars: release the tether, then stimulate collagen in the released space.
Comparative trials cited
- Li X, Fan H, Wang Y, et al. Fractional CO2 laser combined with subcision for three subtypes of atrophic acne scars: retrospective analysis of 413 patients. Lasers Med Sci. 2023;38:195. PubMed.
- Abdelwahab AA, Omar GAB, Hamdino M. Combined subcision with fractional CO2 laser or cross-linked hyaluronic acid versus subcision alone in atrophic post-acne scars. Lasers Med Sci. 2022;38:20. PubMed.
- Salameh F, Shumaker PR, Goodman GJ, et al. Energy-based devices for the treatment of acne scars: 2022 international consensus recommendations. Lasers Surg Med. 2022;54:10-26. Journal.

Dr Gerard Ee
Written, medically reviewed and expert opinion by Dr Gerard Ee, aesthetic doctor and Founder & Medical Director of The Clifford Clinic. This article reflects my clinical experience treating acne scars in Singapore and is intended for general education, not medical advice. Treatment suitability, results, downtime and cost vary from person to person. Please arrange a consultation for advice specific to your skin. Dr Gerard Ee is the Medical Director of The Clifford Clinic, a private clinic in Singapore, and treatments discussed on this site are provided commercially.
Frequently asked questions
Which acne scars are the easiest to treat?
Rolling scars are the easiest, once the band beneath them is released with subcision. They respond better than any other type in the comparative trials, and the reduction in depth can be measured on ultrasound after a single session.
Which acne scars are the hardest to treat?
The hardest are deep, wide, tethered scars in thick skin, together with any scar in skin that darkens easily, where the settings must remain low. Ice pick scars resist lasers but respond well to TCA CROSS.
Can ice pick scars be removed?
They can be improved substantially rather than removed. TCA CROSS produced more than 70 per cent improvement in about three in four patients in the published review, with each pit treated individually over several sessions.
Is fractional CO2 or RF microneedling better for acne scars?
CO2 is slightly more effective in the head-to-head trials. RF microneedling is less painful, heals faster and carries a quarter of the darkening risk. In skin that pigments easily the safer device is usually preferred, or the two are used in sequence.
Why did my laser course leave some scars untouched?
Usually because they were ice pick scars, which a surface laser cannot reach, or rolling scars that were never released. Both require a different technique rather than further sessions of the same one.
Can acne scars be treated on darker skin?
Yes, provided the device and the settings are changed, namely insulated RF microneedling as the opening treatment, lower-energy CO2 or a picosecond laser, and aftercare that reduces darkening. The course takes longer in darker skin.
Which treatment is most effective for depressed acne scars?
The most effective treatment depends on the sub-type. Rolling scars need subcision, ice pick scars usually need TCA CROSS or PDLLA skin booster, and boxcar scars respond to resurfacing and RF microneedling. Most patients need a combination, but not in the same session. I use one modality per session, and the best results come from rotating the modality at the next session, so that different equipment stimulates collagen at different depths and in different layers of the skin.
Can boxcar and ice pick scars be improved with biostimulators?
Both can be improved with biostimulators when the product is matched to the scar. PDLLA skin booster suits boxcar and ice pick scars particularly well, whereas PCL is used for volume loss and PLLA or PDLLA Volume for rolling scars. Biostimulators are matched to the scar type, and outcomes vary between patients.
How do I know what type of acne scar I have?
A light shone across the skin from the side reveals the shape of each scar. Narrow deep pits are ice pick scars, sharp-edged round depressions are boxcar scars, broad wavy depressions are rolling scars, and raised firm lumps are hypertrophic or keloid. A doctor confirms this in person, and self-assessment is unreliable for shallow scars.
Can raised acne scars be treated with microneedling?
Raised scars are not treatable with microneedling. RF microneedling and resurfacing cannot improve keloid or hypertrophic scars, which represent an excess of collagen rather than a deficit. These need a different approach.

Book a consultation with Dr Gerard Ee at The Clifford Clinic
Dr Gerard Ee consults at The Clifford Clinic, 50 Raffles Place, Singapore. Consultations are by appointment. Message the clinic on WhatsApp, or call 6532 2048.
References
Show the key references (16)
1. Kravvas G, Al-Niaimi F. A systematic review of treatments for acne scarring. Part 1: Non-energy-based techniques. Scars Burn Heal. 2017;3:2059513117695312. PubMed
2. Dastgheib M, Heidari S, Azizipour A, et al. Investigating the impact of added Profhilo mesogel to subcision versus subcision monotherapy in treating acne scars; a single-blinded, split-face randomized trial. J Cosmet Dermatol. 2024;23(6):1992-2000. PubMed
3. Abdelwahab AA, Omar GAB, Hamdino M. A combined subcision approach with either fractional CO2 laser (10,600 nm) or cross-linked hyaluronic acid versus subcision alone in atrophic post-acne scar treatment. Lasers Med Sci. 2022;38(1):20. PubMed
4. Ou Y, An G, Liang J, et al. Laser, Microneedling, and Combination Therapies for Moderate to Severe Acne Atrophic Scars: A Systematic Review and Network Meta-Analysis. Aesthetic Plast Surg. 2026. doi:10.1007/s00266-026-06165-8. PubMed
5. Wu B, Gao M, Zhang Y, Bai X. Optimal treatment options for acne scars in patients with historic acne: a systematic review and network meta-analysis. PeerJ. 2025;13:e19938. PubMed
6. Argobi Y, Tobeigei F, Alasiri FI. Fractional CO2 Laser Versus Micro Needling Radiofrequency for Post Acne Scarring: A Meta-Analysis of RCTs. J Cosmet Dermatol. 2026;25(3):e70765. PubMed
7. Ochi H, Tan L, Tan WP, Goh CL. Treatment of Facial Acne Scarring With Fractional Carbon Dioxide Laser in Asians, a Retrospective Analysis of Efficacy and Complications. Dermatol Surg. 2017;43(9):1137-1143. PubMed
8. Sirithanabadeekul P, Tantrapornpong P, Rattakul B, Sutthipisal N, Thanasarnaksorn W. Comparison of Fractional Picosecond 1064-nm Laser and Fractional Carbon Dioxide Laser for Treating Atrophic Acne Scars: A Randomized Split-Face Trial. Dermatol Surg. 2021;47(2):e58-e65. PubMed
9. Cheyasak N, Manuskiatti W, Maneeprasopchoke P, Wanitphakdeedecha R. Topical corticosteroids minimise the risk of postinflammatory hyper-pigmentation after ablative fractional CO2 laser resurfacing in Asians. Acta Derm Venereol. 2015;95(2):201-5. PubMed
10. CROSS technique with 100% TCA for ice pick acne scars: efficacy and safety. PubMed.
11. Chemical reconstruction of skin scars (CROSS) for atrophic scars: a comprehensive review. PubMed.
12. Microneedling in the treatment of atrophic scars: systematic review of randomised controlled trials. PubMed.
13. Platelet-rich plasma augments subcision in atrophic acne scars: split-face comparative study. PubMed.
14. Yi KH, Rosellini I, Lee S, Lee HE. Gas subcision with PDLLA (Juvelook): Evaluating a hybrid mechanical-biologic approach for atrophic acne scars. JPRAS Open. 2026;51:129-133. doi:10.1016/j.jpra.2026.05.001. PMID 42389218.
15. Li X, Fan H, Wang Y, et al. Fractional CO2 laser combined with subcision for three subtypes of atrophic acne scars: retrospective analysis of 413 patients. Lasers Med Sci. 2023;38:195. PubMed.
16. Salameh F, Shumaker PR, Goodman GJ, et al. Energy-based devices for the treatment of acne scars: 2022 international consensus recommendations. Lasers Surg Med. 2022;54:10-26. Journal.
This article is written from published research and my own clinical practice. It is general information and not a substitute for a consultation. Treatment decisions are made after examination.
This page is written from published research and from clinical experience in Singapore since 2012. It is for general education, not medical advice. Whether a treatment suits you, what it may achieve and what it may risk can only be established at a consultation. Dr Gerard Ee is the Medical Director of The Clifford Clinic, a private clinic in Singapore, and treatments discussed on this site are provided commercially.